
Nitrosamines and less-than-lifetime exposure: what the FDA update means to you in practice

Nitrosamines and less-than-lifetime exposure: what the FDA update means to you in practice

At Consult Lhasa, we work through nitrosamine assessments every week, and one question keeps coming up. How do you set an acceptable intake that protects patients without unnecessarily limiting access to medicines taken for weeks or months rather than a lifetime? On 24th September, the US Food and Drug Administration (FDA) provided an answer.

In Application of Less-Than-Lifetime Adjustment to Nitrosamine Impurities, the Center for Drug Evaluation and Research (CDER) confirmed that less-than-lifetime (LTL) adjustment factors from ICH M7(R2) may now be applied to acceptable intake (AI) limits for nitrosamines in products intended for less-than-lifetime use. For treatment of one month or less, the lifetime AI may be multiplied by 80. For more than one month up to 12 months, the factor is 13.3, and for more than one year up to 10 years, it is 6.67. Beyond 10 years, no adjustment applies.
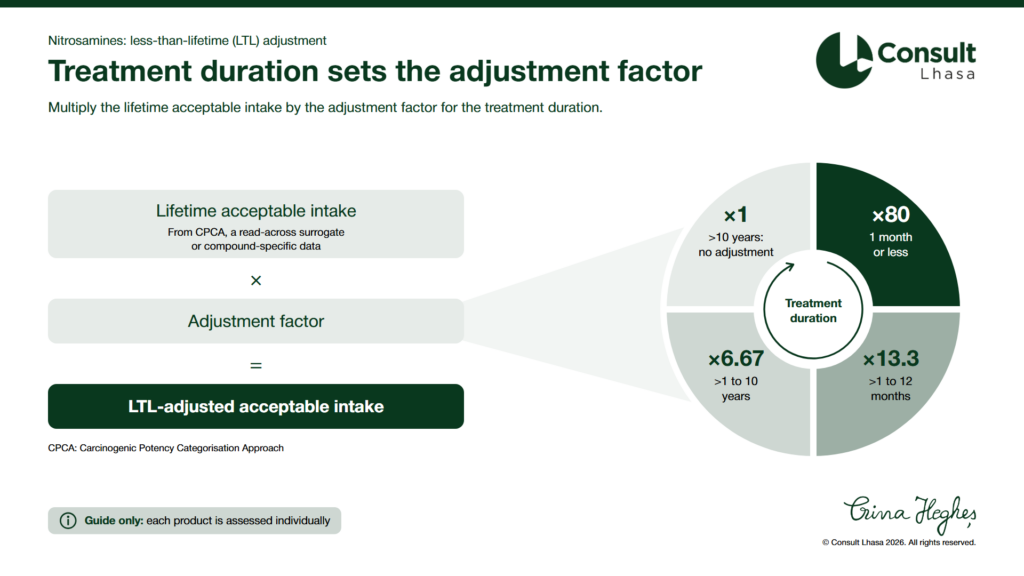
Infographic from Consult Lhasa titled "Treatment duration sets the adjustment factor", about less-than-lifetime (LTL) adjustment for nitrosamines. The subtitle reads: Multiply the lifetime acceptable intake by the adjustment factor for the treatment duration. On the left is an equation: lifetime acceptable intake (from the Carcinogenic Potency Categorisation Approach (CPCA), a read-across surrogate or compound-specific data), multiplied by the adjustment factor, equals the LTL-adjusted acceptable intake. On the right, a circle split into four parts shows the adjustment factor for each treatment duration: 1 month or less, ×80; more than 1 to 12 months, ×13.3; more than 1 to 10 years, ×6.67; more than 10 years, ×1 (no adjustment). Note: guide only, each product is assessed individually. Infographic from Consult Lhasa titled "Scale up the limit, scale up the evidence". It shows four typical less-than-lifetime (LTL) scenarios, from a small uplift on a well supported acceptable intake to a large uplift on a read-across acceptable intake. Check first: the acceptable intake is final, not interim, and treatment duration is 10 years or less. A rising path links four stages, and the further along the path, the stronger the justification needed. The first two stages are often manageable in-house. Straightforward: good compound-specific data, a clear CPCA (Carcinogenic Potency Categorisation Approach) category, one short course as labelled. Needs care: intermittent or repeat dosing, more than one nitrosamine, a vulnerable target population. The last two stages are marked "Build your rationale with Consult Lhasa". Needs an argument: read-across acceptable intake at or below CPCA, one rationale for several agencies, reliable control at the limit. Expert territory: read-across above CPCA, an adjustment factor of ×80 for a potent compound, a weak match backed by docking evidence, weight of evidence. Note: guide only, each product is assessed individually.

This was made possible through science-led collaborations between industry, academia and not-for-profit organisations including Lhasa Limited.

CDER cited two recent papers by Felter et al. (Regulatory Toxicology and Pharmacology, 2025 and 2026), developed in part through the Health and Environmental Sciences Institute (HESI) Nitrosamines Research Program, which directly addressed open questions on cumulative dose response, DNA repair capacity and polypharmacy.

Dr David Ponting DABT represented both Lhasa Limited and Consult Lhasa on this work.

One of the fundamental axioms of toxicology is that the dose makes the poison. As a result, it can generally be assumed that a lower exposure, e.g. taking a drug for a shorter time, reduces the risk – the FDA have now accepted this argumentation for nitrosamines.

Dr David Ponting DABT, Lead Scientific Consultant

Dr David Ponting DABT Lead Scientific Consultant

What does LTL mean for patient safety?

CDER’s response to emerging scientific evidence, and its openness to evidence and arguments that can justify an appropriate safe limit, is to be applauded.

But this does not mean any lowering of the level of patient protection; on the contrary, we should expect careful inspection of any proposal to use the LTL approach. Applying an LTL factor results in the scaling (by multiplication) of the lifetime value, making both the robustness of this starting value and the specific context of use more important. This value can come from the Carcinogenic Potency Categorisation Approach (CPCA), a read-across surrogate or from compound-specific data.

How should industry respond?

From a regulator’s perspective, the larger the scaling factor or the more vulnerable the expected patient population, the stronger the evidence dossier needed. From industry’s perspective, some scenarios will be easier to tackle than others. The graphic below shows some simpler situations and some where there is an advantage in seeking the support of an external expert.
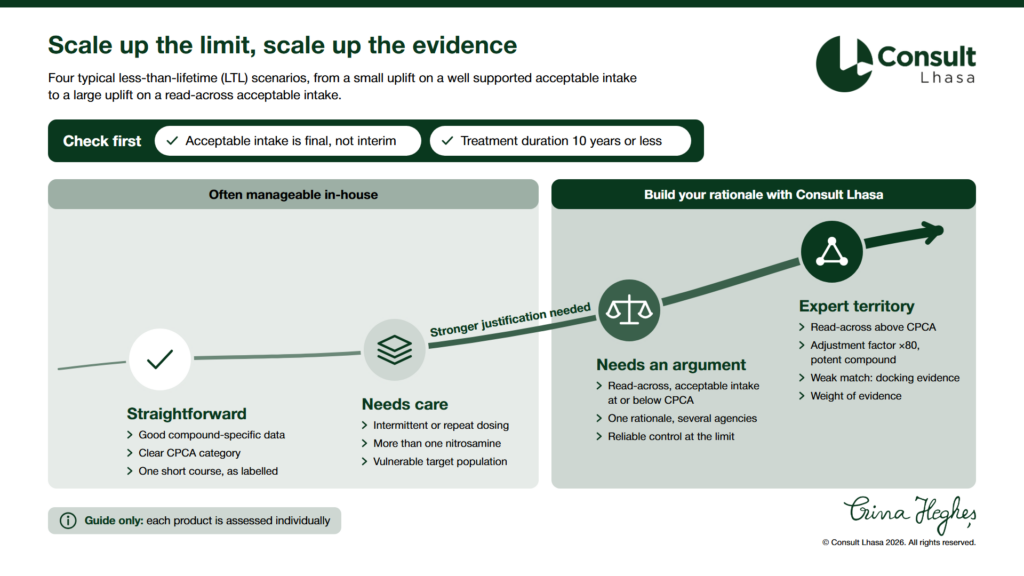
Infographic from Consult Lhasa titled "Scale up the limit, scale up the evidence". It shows four typical less-than-lifetime (LTL) scenarios, from a small uplift on a well supported acceptable intake to a large uplift on a read-across acceptable intake. Check first: the acceptable intake is final, not interim, and treatment duration is 10 years or less. A rising path links four stages, and the further along the path, the stronger the justification needed. The first two stages are often manageable in-house. Straightforward: good compound-specific data, a clear CPCA (Carcinogenic Potency Categorisation Approach) category, one short course as labelled. Needs care: intermittent or repeat dosing, more than one nitrosamine, a vulnerable target population. The last two stages are marked "Build your rationale with Consult Lhasa". Needs an argument: read-across acceptable intake at or below CPCA, one rationale for several agencies, reliable control at the limit. Expert territory: read-across above CPCA, an adjustment factor of ×80 for a potent compound, a weak match backed by docking evidence, weight of evidence. Note: guide only, each product is assessed individually.

This is where Consult Lhasa can help. Our consultants support organisations with surrogate selection and acceptable intake strategy, including CPCA and read-across, and with docking-based mechanistic evidence where a weight-of-evidence case is needed. Together, those form the scientific foundation an LTL proposal will rest on. We support submissions to regulatory authorities worldwide, building each rationale around the specific problem and the expectations of the agencies involved.

Contact Consult Lhasa

If you would like to discuss your acceptable intake strategy speak to our consultants today.

Share this post

Latest posts

16 March 2026
Author: Dr Arianne Rivellis, Dr. Gabriela Silveira, Dr Martyn Chilton DABT and Upasana Sonigra
8 March 2026
Author: Upasana Sonigra



